Clinical Focus ›› 2026, Vol. 41 ›› Issue (8): 677-684.doi: 10.3969/j.issn.1004-583X.2026.08.001
Network meta-analysis of the risk of urinary tract infection in patients with type 2 diabetes mellitus treated with different doses of SGLT-2 inhibitors
Zhou Yu, Deng Liping( ), Hu Jun, Shou Yueying, Wu Meng, Gao Jieting, Li Wei
Department of Pharmacy ,the First People’s Hospital of Pinghu Pinghu 314200, China
-
Received:2026-04-21Online:2026-08-20Published:2026-08-25 -
Contact:Deng Liping E-mail:1473040098@qq.com

CLC Number:
Cite this article
Zhou Yu, Deng Liping, Hu Jun, Shou Yueying, Wu Meng, Gao Jieting, Li Wei. Network meta-analysis of the risk of urinary tract infection in patients with type 2 diabetes mellitus treated with different doses of SGLT-2 inhibitors[J]. Clinical Focus, 2026, 41(8): 677-684.
share this article
Add to citation manager EndNote|Ris|BibTeX
URL: https://www.lchc.cn/EN/10.3969/j.issn.1004-583X.2026.08.001
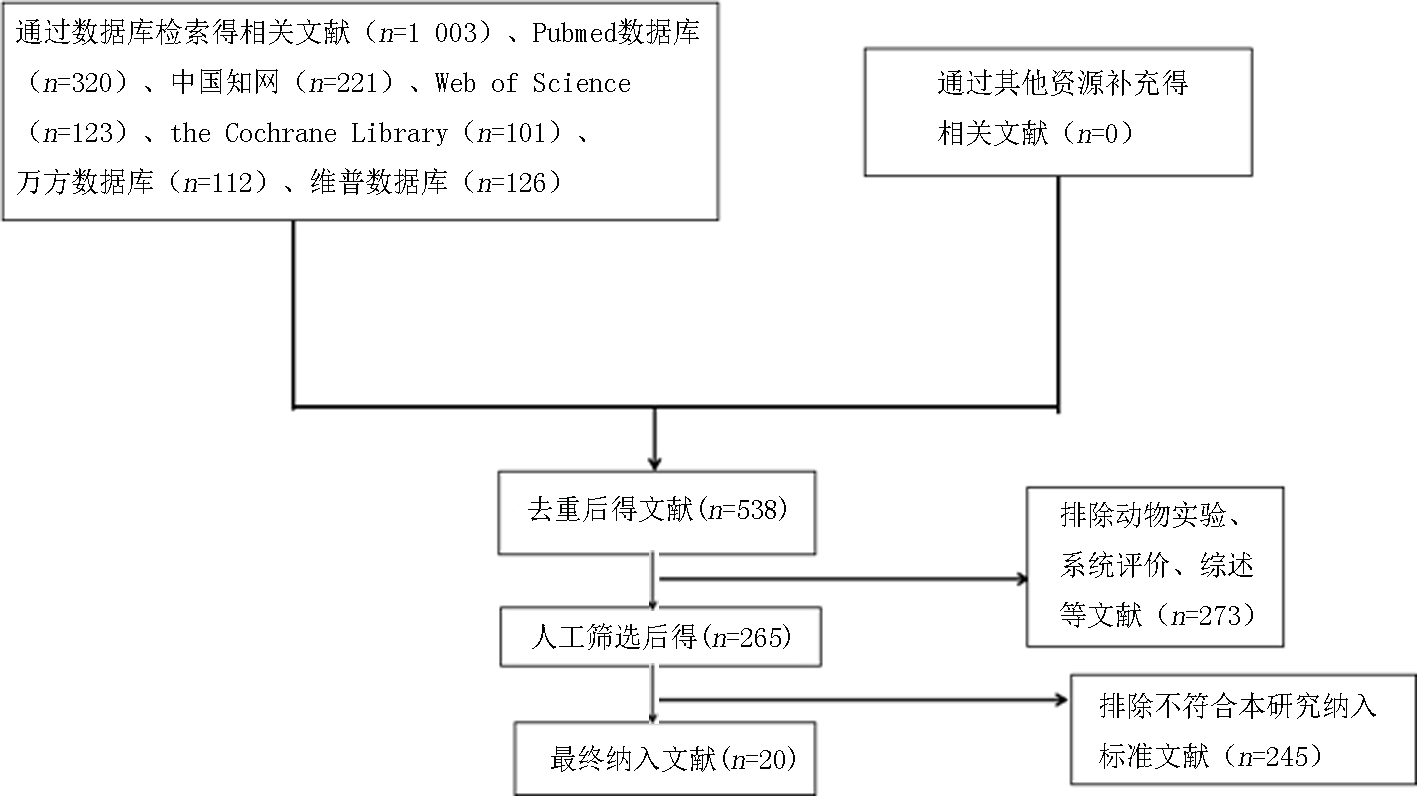
Fig.1 Flowchart of literature screening
| 纳入研究 | 样本量 (例) | 试验组 | 对照组 | 基础治疗 | 疗程 (周) | 病程 (年) | 随访时间 (周) | 平均年龄 (岁) |
|---|---|---|---|---|---|---|---|---|
| Weng 2021[ | 483 | 恒格列净5 mg | 安慰剂 | 二甲双胍 | 24 | / | 4 | 55 |
| 恒格列净10 mg | ||||||||
| Ferrannini 2013[ | 326 | 恩格列净5 mg | 安慰剂 | 无 | 12 | / | / | 58 |
| 恩格列净10 mg | ||||||||
| 恩格列净25 mg | ||||||||
| Yale 2017[ | 215 | 卡格列净100 mg | 安慰剂 | 无 | 18 | 10 | 52 | 65 |
| 卡格列净300 mg | ||||||||
| Strojek 2014[ | 596 | 达格列净2.5 mg | 安慰剂 | 格列美脲 | 48 | 7 | / | 60 |
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Wilding2014[ | 800 | 达格列净2.5 mg | 安慰剂 | 胰岛素 | 24 | 14 | 104 | 60 |
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Kaku 2013[ | 279 | 达格列净1 mg | 安慰剂 | 无 | 12 | 5 | / | 57 |
| 达格列净2.5 mg | ||||||||
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Rosenstock 2013[ | 424 | 恩格列净1 mg | 安慰剂 | 二甲双胍 | 12 | / | / | 59 |
| 恩格列净5 mg | ||||||||
| 恩格列净10 mg | ||||||||
| 恩格列净25 mg | ||||||||
| 恩格列净50 mg | ||||||||
| Amin 2015[ | 273 | 艾托格列净1 mg | 安慰剂 | 无 | 12 | 23 | / | 55 |
| 艾托格列净5 mg | ||||||||
| 艾托格列净10 mg | ||||||||
| 艾托格列净25 mg | ||||||||
| Wilding 2013[ | 469 | 达格列净2.5 mg | 安慰剂 | 无 | 26 | 10 | / | 57 |
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Yamout 2014[ | 1085 | 卡格列净100 mg | 安慰剂 | 无 | 12 | 15 | / | 67 |
| 卡格列净300 mg | ||||||||
| Stenlof 2013[ | 584 | 卡格列净100 mg | 安慰剂 | 无 | 26 | 4 | / | 55 |
| 卡格列净300 mg | ||||||||
| Yale 2014[ | 269 | 卡格列净100 mg | 安慰剂 | 无 | 52 | / | / | 69 |
| 卡格列净300 mg | ||||||||
| Bode 2013[ | 714 | 卡格列净100 mg | 安慰剂 | 无 | 26 | 12 | / | 64 |
| 卡格列净300 mg | ||||||||
| Yang 2016[ | 449 | 达格列净5 mg | 安慰剂 | 二甲双胍 | 24 | 5 | / | 53 |
| 达格列净10 mg | ||||||||
| Liu 2020[ | 455 | 艾托格列净5 mg | 安慰剂 | 格列美脲 | 52 | 8 | / | 56 |
| 艾托格列净15 mg | ||||||||
| Kovacs 2014[ | 498 | 恩格列净10 mg | 安慰剂 | 吡格列酮±二甲双胍 | 24 | / | / | 54 |
| 恩格列净25 mg | ||||||||
| Rosenstock 2014[ | 563 | 恩格列净10 mg | 安慰剂 | 胰岛素 | 52 | / | / | / |
| 恩格列净25 mg | ||||||||
| Strojek 2011[ | 438 | 达格列净2.5 mg | 安慰剂 | 格列美脲 | 24 | 7 | / | 60 |
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Terra 2017[ | 461 | 艾托格列净5 mg | 安慰剂 | 无 | 52 | 5 | / | 56 |
| 艾托格列净15 mg | ||||||||
| Ji 2019[ | 506 | 艾托格列净5 mg | 安慰剂 | 二甲双胍 | 26 | 7 | / | 56 |
| 艾托格列净15 mg |
Tab.1 Basic characteristics of the included studies
| 纳入研究 | 样本量 (例) | 试验组 | 对照组 | 基础治疗 | 疗程 (周) | 病程 (年) | 随访时间 (周) | 平均年龄 (岁) |
|---|---|---|---|---|---|---|---|---|
| Weng 2021[ | 483 | 恒格列净5 mg | 安慰剂 | 二甲双胍 | 24 | / | 4 | 55 |
| 恒格列净10 mg | ||||||||
| Ferrannini 2013[ | 326 | 恩格列净5 mg | 安慰剂 | 无 | 12 | / | / | 58 |
| 恩格列净10 mg | ||||||||
| 恩格列净25 mg | ||||||||
| Yale 2017[ | 215 | 卡格列净100 mg | 安慰剂 | 无 | 18 | 10 | 52 | 65 |
| 卡格列净300 mg | ||||||||
| Strojek 2014[ | 596 | 达格列净2.5 mg | 安慰剂 | 格列美脲 | 48 | 7 | / | 60 |
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Wilding2014[ | 800 | 达格列净2.5 mg | 安慰剂 | 胰岛素 | 24 | 14 | 104 | 60 |
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Kaku 2013[ | 279 | 达格列净1 mg | 安慰剂 | 无 | 12 | 5 | / | 57 |
| 达格列净2.5 mg | ||||||||
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Rosenstock 2013[ | 424 | 恩格列净1 mg | 安慰剂 | 二甲双胍 | 12 | / | / | 59 |
| 恩格列净5 mg | ||||||||
| 恩格列净10 mg | ||||||||
| 恩格列净25 mg | ||||||||
| 恩格列净50 mg | ||||||||
| Amin 2015[ | 273 | 艾托格列净1 mg | 安慰剂 | 无 | 12 | 23 | / | 55 |
| 艾托格列净5 mg | ||||||||
| 艾托格列净10 mg | ||||||||
| 艾托格列净25 mg | ||||||||
| Wilding 2013[ | 469 | 达格列净2.5 mg | 安慰剂 | 无 | 26 | 10 | / | 57 |
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Yamout 2014[ | 1085 | 卡格列净100 mg | 安慰剂 | 无 | 12 | 15 | / | 67 |
| 卡格列净300 mg | ||||||||
| Stenlof 2013[ | 584 | 卡格列净100 mg | 安慰剂 | 无 | 26 | 4 | / | 55 |
| 卡格列净300 mg | ||||||||
| Yale 2014[ | 269 | 卡格列净100 mg | 安慰剂 | 无 | 52 | / | / | 69 |
| 卡格列净300 mg | ||||||||
| Bode 2013[ | 714 | 卡格列净100 mg | 安慰剂 | 无 | 26 | 12 | / | 64 |
| 卡格列净300 mg | ||||||||
| Yang 2016[ | 449 | 达格列净5 mg | 安慰剂 | 二甲双胍 | 24 | 5 | / | 53 |
| 达格列净10 mg | ||||||||
| Liu 2020[ | 455 | 艾托格列净5 mg | 安慰剂 | 格列美脲 | 52 | 8 | / | 56 |
| 艾托格列净15 mg | ||||||||
| Kovacs 2014[ | 498 | 恩格列净10 mg | 安慰剂 | 吡格列酮±二甲双胍 | 24 | / | / | 54 |
| 恩格列净25 mg | ||||||||
| Rosenstock 2014[ | 563 | 恩格列净10 mg | 安慰剂 | 胰岛素 | 52 | / | / | / |
| 恩格列净25 mg | ||||||||
| Strojek 2011[ | 438 | 达格列净2.5 mg | 安慰剂 | 格列美脲 | 24 | 7 | / | 60 |
| 达格列净5 mg | ||||||||
| 达格列净10 mg | ||||||||
| Terra 2017[ | 461 | 艾托格列净5 mg | 安慰剂 | 无 | 52 | 5 | / | 56 |
| 艾托格列净15 mg | ||||||||
| Ji 2019[ | 506 | 艾托格列净5 mg | 安慰剂 | 二甲双胍 | 26 | 7 | / | 56 |
| 艾托格列净15 mg |
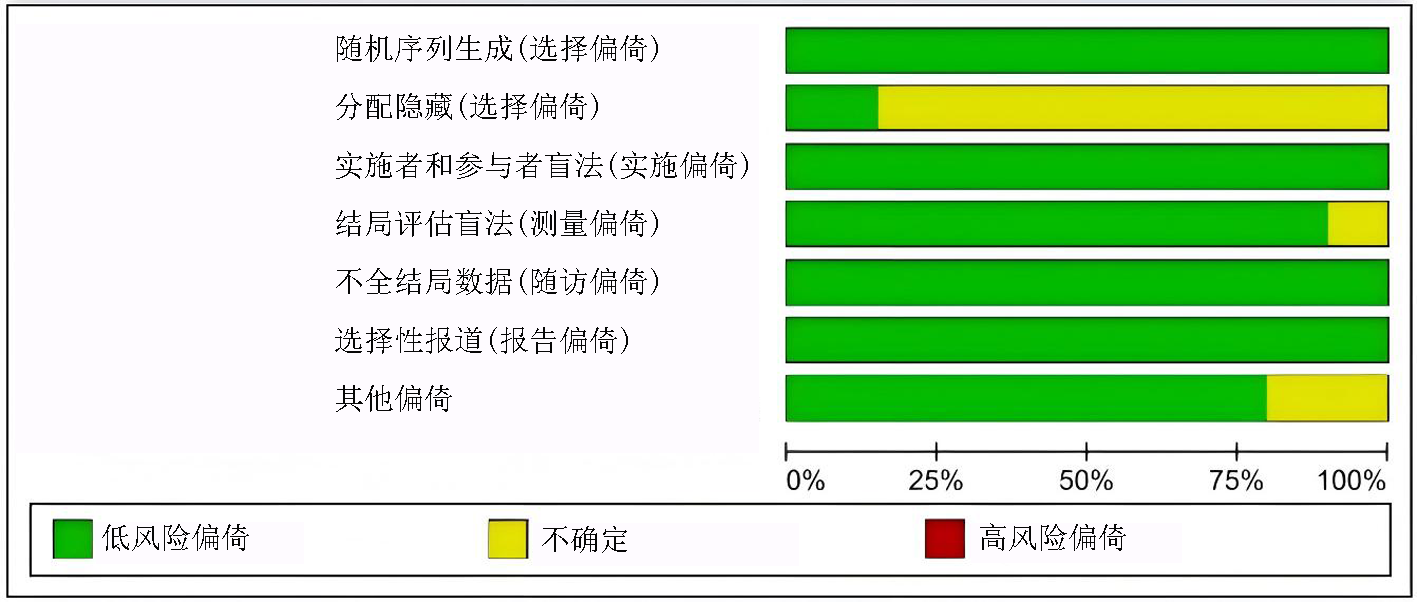
Fig.2 Risk of bias graph for the included studies
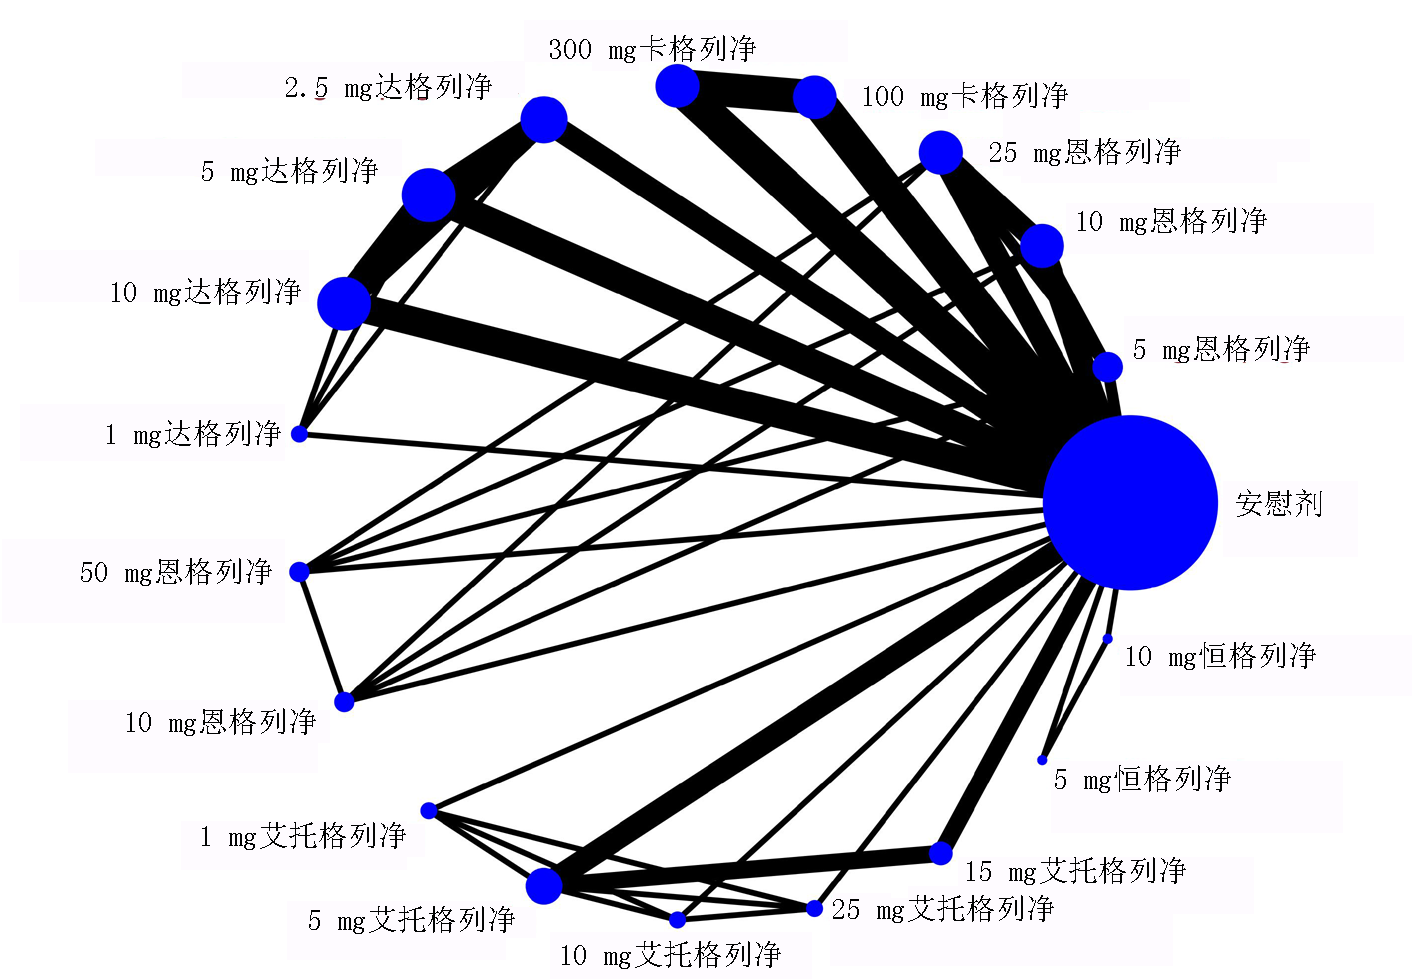
Fig.3 Network plot of the included studies
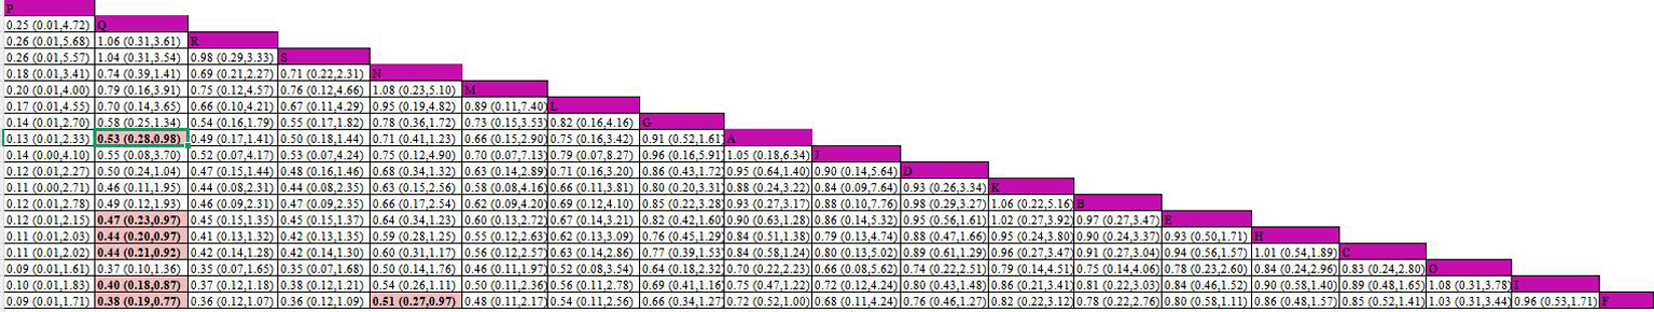
Fig.4 League table of the network meta-analysis of urinary tract infection risk (RR[95% CI]) Note:A:Placebo;B:5 mg empagliflozin;C:10 mg empagliflozin;D:25 mg empagliflozin;E:100 mg Canagliflozin;F:300 mg Canagliflozin;G:2.5 mg Dapagliflozin;H:5 mg Dapagliflozin;I:10 mg Dapagliflozin;J:1 mg Dapagliflozin;K:50 mg empagliflozin;L:1 mg empagliflozin;M:1 mg Ertugliflozin;N:5 mg Ertugliflozin;O:10 mg Ertugliflozin;P:25 mg Ertugliflozin;Q:15 mg Ertugliflozin;R:5 mg Henagliflozin;S:10 mg Henagliflozin。
| 干预措施 | SUCRA | PrBest | MeanRank |
|---|---|---|---|
| 25 mg艾托格列净 | 89.3 | 68.8 | 2.9 |
| 15 mg艾托格列净 | 79.9 | 2.9 | 4.6 |
| 5 mg恒格列净 | 77.6 | 6.8 | 5 |
| 10 mg恒格列净 | 77.3 | 6.5 | 5.1 |
| 5 mg艾托格列净 | 66.7 | 0.3 | 7 |
| 1 mg艾托格列净 | 62.4 | 4.2 | 7.8 |
| 1 mg恩格列净 | 57.6 | 4.7 | 8.6 |
| 1 mg达格列净 | 52.6 | 0 | 9.5 |
| 安慰剂 | 47.5 | 0 | 10.5 |
| 2.5 mg达格列净 | 47.4 | 4.2 | 10.5 |
| 25 mg恩格列净 | 41.7 | 0 | 11.5 |
| 50 mg恩格列净 | 39 | 0.9 | 12 |
| 5 mg恩格列净 | 38.9 | 0.5 | 12 |
| 100 mg卡格列净 | 38.3 | 0 | 12.1 |
| 5 mg达格列净 | 31.9 | 0 | 13.3 |
| 10 mg恩格列净 | 31.5 | 0 | 13.3 |
| 10 mg艾托格列净 | 27 | 0.1 | 14.1 |
| 10 mg达格列净 | 24 | 0 | 14.7 |
| 300 mg卡格列净 | 19.7 | 0 | 15.5 |
Tab.2 Ranking of urinary tract infection risk
| 干预措施 | SUCRA | PrBest | MeanRank |
|---|---|---|---|
| 25 mg艾托格列净 | 89.3 | 68.8 | 2.9 |
| 15 mg艾托格列净 | 79.9 | 2.9 | 4.6 |
| 5 mg恒格列净 | 77.6 | 6.8 | 5 |
| 10 mg恒格列净 | 77.3 | 6.5 | 5.1 |
| 5 mg艾托格列净 | 66.7 | 0.3 | 7 |
| 1 mg艾托格列净 | 62.4 | 4.2 | 7.8 |
| 1 mg恩格列净 | 57.6 | 4.7 | 8.6 |
| 1 mg达格列净 | 52.6 | 0 | 9.5 |
| 安慰剂 | 47.5 | 0 | 10.5 |
| 2.5 mg达格列净 | 47.4 | 4.2 | 10.5 |
| 25 mg恩格列净 | 41.7 | 0 | 11.5 |
| 50 mg恩格列净 | 39 | 0.9 | 12 |
| 5 mg恩格列净 | 38.9 | 0.5 | 12 |
| 100 mg卡格列净 | 38.3 | 0 | 12.1 |
| 5 mg达格列净 | 31.9 | 0 | 13.3 |
| 10 mg恩格列净 | 31.5 | 0 | 13.3 |
| 10 mg艾托格列净 | 27 | 0.1 | 14.1 |
| 10 mg达格列净 | 24 | 0 | 14.7 |
| 300 mg卡格列净 | 19.7 | 0 | 15.5 |
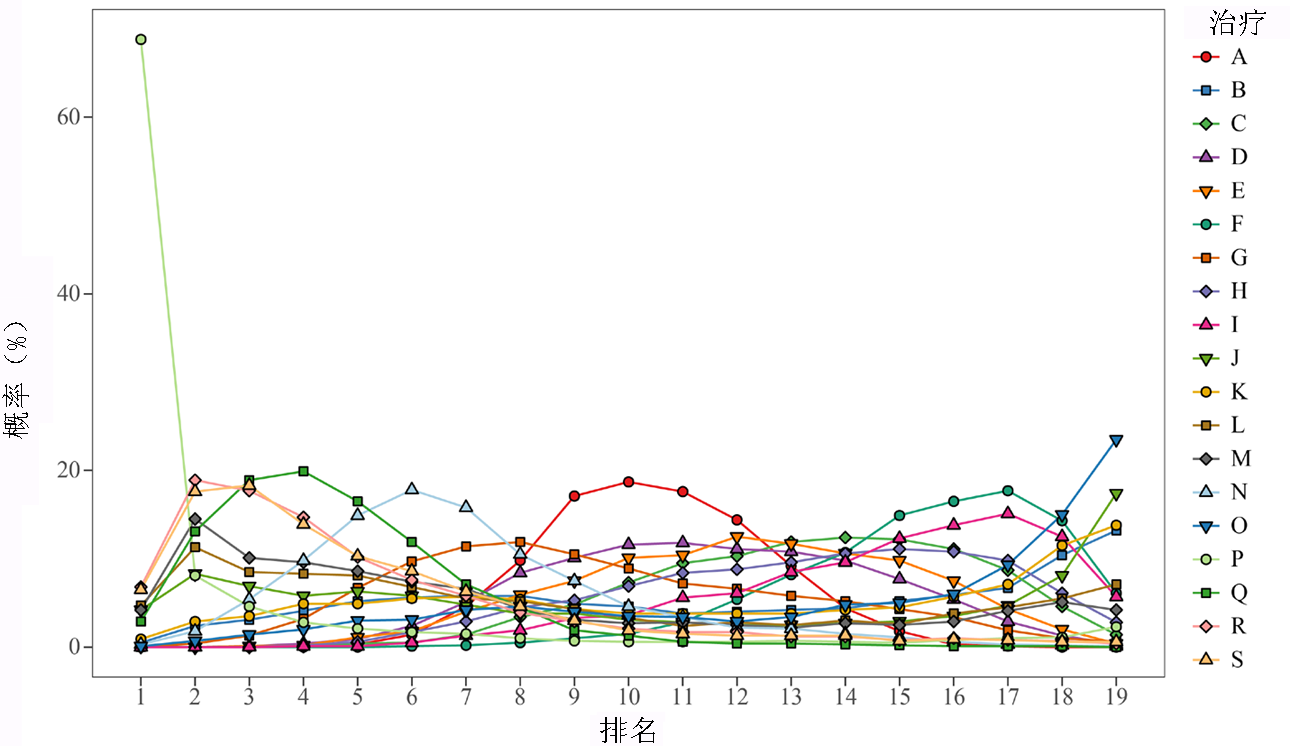
Fig.5 Probability ranking of urinary tract infection risk Note:A:Placebo;B:5 mg empagliflozin;C:10 mg empagliflozin;D:25 mg empagliflozin;E:100 mg Canagliflozin;F:300 mg Canagliflozin;G:2.5 mg Dapagliflozin;H:5 mg Dapagliflozin;I:10 mg Dapagliflozin;J:1 mg Dapagliflozin;K:50 mg empagliflozin;L:1 mg empagliflozin;M:1 mg Ertugliflozin;N:5 mg Ertugliflozin;O:10 mg Ertugliflozin;P:25 mg Ertugliflozin;Q:15 mg Ertugliflozin;R:5 mg Henagliflozin;S:10 mg Henagliflozin。
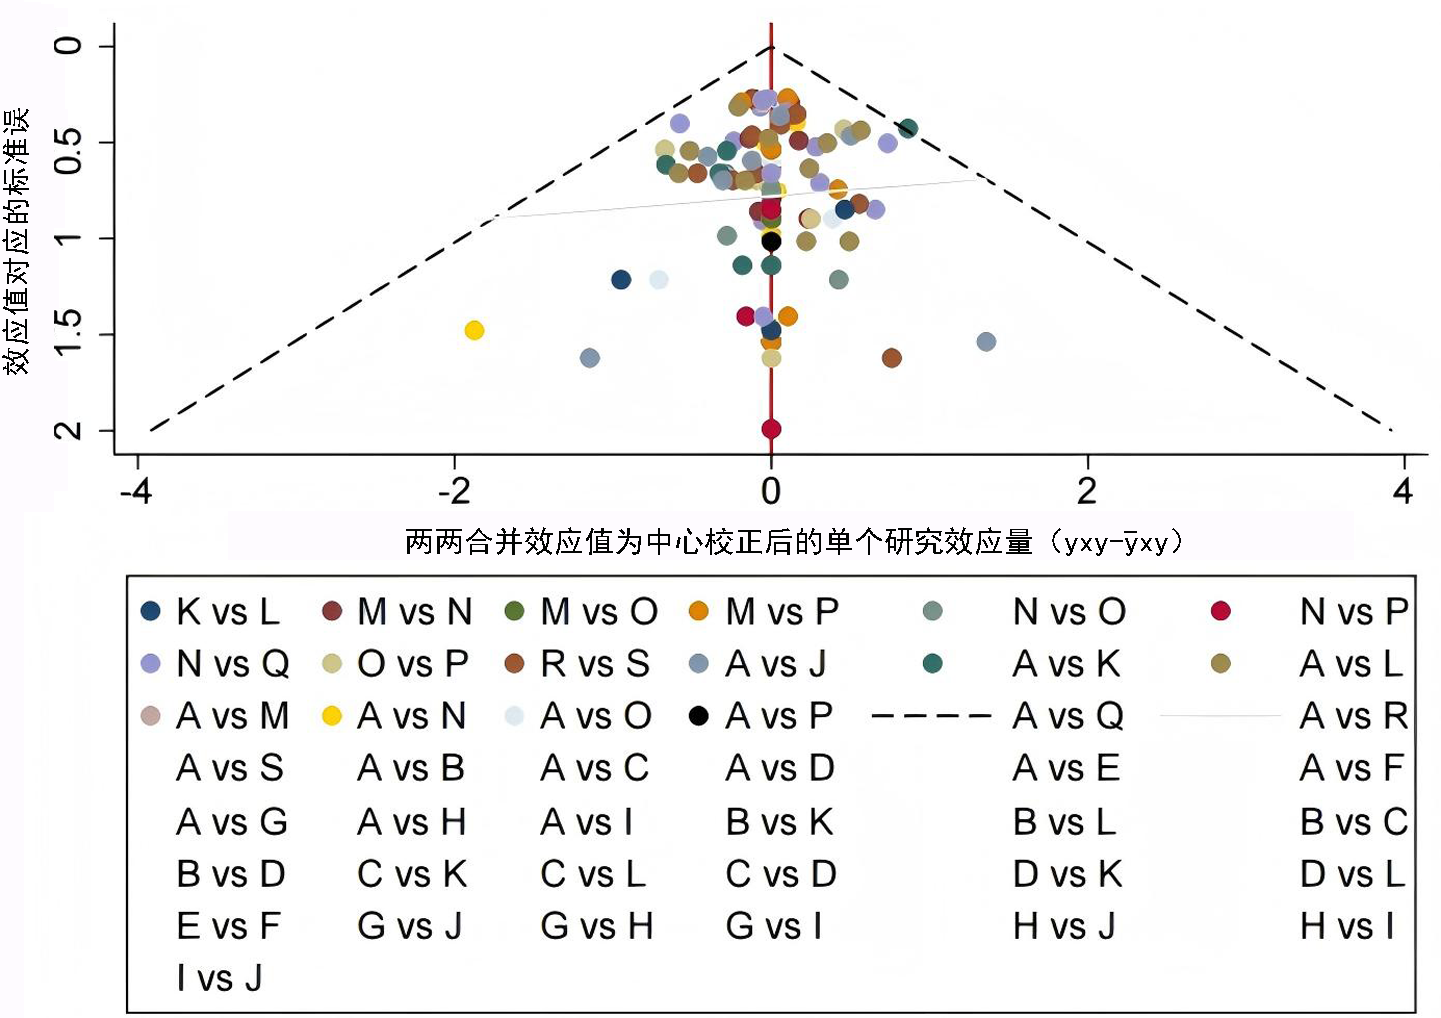
Fig.6 Funnel plot of the risk of urinary tract infection Note:A:Placebo;B:5 mg empagliflozin;C:10 mg empagliflozin;D:25 mg empagliflozin;E:100 mg Canagliflozin;F:300 mg Canagliflozin;G:2.5 mg Dapagliflozin;H:5 mg Dapagliflozin;I:10 mg Dapagliflozin;J:1 mg Dapagliflozin;K:50 mg empagliflozin;L:1 mg empagliflozin;M:1 mg Ertugliflozin;N:5 mg Ertugliflozin;O:10 mg Ertugliflozin;P:25 mg Ertugliflozin;Q:15 mg Ertugliflozin;R:5 mg Henagliflozin;S:10 mg Henagliflozin。
| [1] | 中华医学会糖尿病学分会. 中国糖尿病防治指南:2024版[J]. 中华糖尿病杂志, 2025, 17(1):16-139.doi:10.3760/cma.j.cn115791-20241203-00705. |
| [2] | 潘慧敏, 王钰博, 单慧亭, 等. SGLT-2抑制剂治疗2型糖尿病的快速卫生技术评估[J]. 中国药房, 2025, 36(23):2978-2984.doi:10.6039/j.issn.1001-0408.2025.23.17. |
| [3] | Yang SW, Liu Y, Zhang SZ, et al. Risk of diabetic ketoacidosis of SGLT2 inhibitors in patients with type 2diabetes:A systematic review and network meta-analysis of randomized controlled trials[J]. Front Pharmacol, 2023, 14:1145587.doi:10.3389/FPHAR.2023.1145587. |
| [4] | 刘凤琪, 柴三葆, 赵厚宇, 等. 钠-葡萄糖共转运蛋白2抑制剂引起2型糖尿病患者尿路或生殖器感染风险的网状Meta分析[J]. 中华糖尿病杂志, 2022, 14(8):799-808.doi:10.3760/cma.j.cn115791-20211217-00668. |
| [5] | 俞匀, 智俊娜. 老年2型糖尿病病人SGLT-2抑制剂应用专家共识[J]. 实用老年医学, 2023, 37(08):865-872.doi:10.3969/j.issn.1003-9198.2023.08.027. |
| [6] | 纪立农, 郭立新, 郭晓蕙, 等. 钠-葡萄糖共转运蛋白2(SGLT2)抑制剂临床合理应用中国专家建议[J]. 中国糖尿病杂志, 2016, 24(10):865-870.doi:10.3969/j.issn.1006-6187.2016.10.01. |
| [7] | 蔡美玲, 林枝兵, 俞惠翻, 等. 卡格列净治疗2型糖尿病出现尿路感染风险的系统评价[J]. 中国医院用药评价与分析, 2025, 25(10):1224-1227.doi:10.14009/j.issn.1672-2124.2025.10.016. |
| [8] | Weng J, Zeng L, Zhang Y, et al. Henagliflozin as add-on therapy to metformin in patients with type 2 diabetes inadequately controlled with metformin: A multicentre, randomized, double-blind, placebo-controlled, phase 3trial[J]. Diabetes Obes Metab, 2021, 23(8):1754-1764.doi:10.1111/DOM.14389. |
| [9] |
Ferrannini E, Seman L, Seewaldt-Becker E, et al. A Phase IIb, randomized, placebo-controlled study of the SGLT2 inhibitor empagliflozin in patients with type 2 diabetes[J]. Diabetes Obes Metab, 2013, 15(8):721-728.doi:10.1111/dom.12081.
pmid: 23398530 |
| [10] | Yale JF, Xie J, Sherman SE, et al. Canagliflozin in conjunction with sulfonylurea maintains glycemic control and weight loss over 52 weeks: A randomized, controlled trial in patients with type 2 diabetes mellitus[J]. Clin Ther, 2017, 39(11):2230-2242.e2.doi:10.1016/j.clinthera.2017.10.003. |
| [11] | Strojek K, Yoon KH, Hruba V, et al. Dapagliflozin added to glimepiride in patients with type 2 diabetes mellitus sustains glycemic control and weight loss over 48 weeks: A randomized, double-blind, parallel-group, placebo-controlled trial[J]. Diabetes Ther, 2014, 5(1):267-283.doi:10.1007/s13300-014-0072-0. |
| [12] |
Wilding JP, Woo V, Rohwedder K, et al. Dapagliflozin in patients with type 2 diabetes receiving high doses of insulin: Efficacy and safety over 2 years[J]. Diabetes Obes Metab, 2014, 16(2):124-136.doi:10.1111/dom.12187.
pmid: 23911013 |
| [13] |
Kaku K, Inoue S, Matsuoka O, et al. Efficacy and safety of dapagliflozin as a monotherapy for type 2 diabetes mellitus in Japanese patients with inadequate glycaemic control:A phase II multicentre, randomized, double-blind, placebo-controlled trial[J]. Diabetes Obes Metab, 2013, 15(5):432-440.doi:10.1111/dom.12047.
pmid: 23194084 |
| [14] |
Rosenstock J, Seman LJ, Jelaska A, et al. Efficacy and safety of empagliflozin, a sodium glucose cotransporter 2 (SGLT2) inhibitor, as add-on to metformin in type 2 diabetes with mild hyperglycaemia[J]. Diabetes Obes Metab, 2013, 15(12):1154-1160.doi:10.1111/dom.12185.
pmid: 23906374 |
| [15] |
Amin NB, Wang X, et al. Dose-ranging efficacy and safety study of ertugliflozin, a sodium-glucose co-transporter 2 inhibitor, in patients with type 2 diabetes on a background of metformin[J]. Diabetes Obes Metab, 2015, 17(6):591-598.doi:10.1111/dom.12460.
pmid: 25754396 |
| [16] |
Wilding JP, Charpentier G, Hollander P, et al. Efficacy and safety of canagliflozin in patients with type 2 diabetes mellitus inadequately controlled with metformin and sulphonylurea: A randomised trial[J]. Int J Clin Pract, 2013, 67(12):1267-1282.doi:10.1111/ijcp.12322.
pmid: 24118688 |
| [17] |
Yamout H, Perkovic V, Davies M, et al. Efficacy and safety of canagliflozin in patients with type 2 diabetes and stage 3 nephropathy[J]. Am J Nephrol, 2014, 40(1):64-74.doi:10.1159/000364909.
pmid: 25059406 |
| [18] |
Stenlöf K, Cefalu WT, Kim KA, et al. Efficacy and safety of canagliflozin monotherapy in subjects with type 2 diabetes mellitus inadequately controlled with diet and exercise[J]. Diabetes Obes Metab, 2013, 15(4):372-382.doi:10.1111/dom.12054.
pmid: 23279307 |
| [19] |
Yale JF, Bakris G, Cariou B, et al. Efficacy and safety of canagliflozin over 52 weeks in patients with type 2 diabetes mellitus and chronic kidney disease[J]. Diabetes Obes Metab, 2014, 16(10):1016-1027.doi:10.1111/dom.12348.
pmid: 24965700 |
| [20] | Bode B, Stenlöf K, Sullivan D, et al. Efficacy and safety of canagliflozin treatment in older subjects with type 2 diabetes mellitus: A randomized trial[J]. Hosp Pract, 2013, 41(2):72-8410.38. doi:10/hp.2013.04.1020. |
| [21] | Yang W, Han P, Min KW, et al. Efficacy and safety of dapagliflozin in Asian patients with type 2 diabetes after metformin failure: A randomized controlled trial[J]. JDiabetes, 2016, 8(6):796-808.doi:10.1111/dom.12348. |
| [22] |
Liu J, Patel S, Cater NB, et al. Efficacy and safety of ertugliflozin in East/Southeast Asian patients with type 2 diabetes mellitus[J]. Diabetes Obes Metab, 2020, 22(4):574-582.doi:10.1111/dom.13931.
pmid: 31797522 |
| [23] |
Kovacs CS, Seshiah V, Swallow R, et al. Empagliflozin improves glycaemic and weight control as add-on therapy to pioglitazone or pioglitazone plus metformin in patients with type 2 diabetes:A 24-week, randomized, placebo-controlled trial[J]. Diabetes Obes Metab, 2014, 16(2):147-158.doi:10.1111/dom.12188.
pmid: 23906415 |
| [24] |
Rosenstock J, Jelaska A, Frappin G, et al. Improved glucose control with weight loss, lower insulin doses, and no increased hypoglycemia with empagliflozin added to titrated multiple daily injections of insulin in obese inadequately controlled type 2 diabetes[J]. Diabetes Care, 2014, 37(7):1815-1823.doi:10.2337/dc13-3055.
pmid: 24929430 |
| [25] | Strojek K, Yoon KH, Hruba V, et al. Effect of dapagliflozin in patients with type 2 diabetes who have inadequate glycaemic control with glimepiride: A randomized, 24-week, double-blind, placebo-controlled trial[J]. Diabetes Obes Metab, 2011, 13(10):928-938.doi:10.1111/j.1463-1326.2011.01434.x. |
| [26] |
Terra SG, Focht K, Davies M, et al. Phase III, efficacy and safety study of ertugliflozin monotherapy in people with type 2 diabetes mellitus inadequately controlled with diet and exercise alone[J]. Diabetes Obes Metab, 2017, 19(5):721-728.doi:10.1111/dom.12888.
URL pmid: 28116776 |
| [27] |
Ji L, Liu Y, Miao H, et al. Safety and efficacy of ertugliflozin in Asian patients with type 2 diabetes mellitus inadequately controlled with metformin monotherapy: VERTIS Asia[J]. Diabetes Obes Metab, 2019, 21(6):1474-1482.doi:10.1111/dom.13681.
pmid: 30830724 |
| [28] | 石晓妍, 赵卫民. 基于钠-葡萄糖协同转运蛋白2抑制剂应用的糖尿病患者尿路感染高危因素识别与管理[J]. 大医生, 2025, 10(22):126-129.doi:10.3969/j.issn.2096-2665.2025.22.035. |
| [29] | Malik A, Ahmed E, Hamid S, et al. Euglycemic diabetic ketoacidosis (DKA) with sodium-glucose transport protein 2 (SGLT-2)inhibitors[J]. Cureus, 2025, 17(2):e79309.doi:10.7759/CUREUS.79309. |
| [30] | Mohammad H, Arihant S, Mehul S, et al. Recurrent urinary tract infection associated with SGLT-2 inhibitor in type 2 diabetes mellitus patient: A case report[J]. Clin Case Rep, 2023, 11(1):e6803.doi:10.1002/CCR3.6803. |
| [31] |
Rouse B, Chaimani A, Li T. Network meta-analysis: an introduction for clinicians[J]. Intern Emerg Med, 2017, 12(1):103-111.doi:10.1007/s11739-016-1583-7.
pmid: 27913917 |
| [32] | 赵玉红, 颜蕾, 宁思思, 等. 服用达格列净致尿路感染1例报告[J]. 基层医学论坛, 2023, 27(02):12-15.doi:10.19435/j.1672-1721.2023.02.004. |
| [33] | Chen L, Xue Q, Yan C, et al. Comparative safety of different recommended doses of sodium-glucose cotransporter 2 inhibitors in patients with type 2 diabetes mellitus: A systematic review and network meta-analysis of randomized clinical trials[J]. Front Endocrinol (Lausanne), 2023, 14:1256548. doi:10.3389/fendo.2023.1256548. |
| [34] | Donnan JR, Grandy CA, Chibrikov E, et al. Dose response of sodium glucose cotransporter-2 inhibitors in relation to urinary tract infections: A systematic review and network meta-analysis of randomized controlled trials[J]. CMAJ open, 2018, 6(4):E594-E602.doi:10.9778/cmajo.20180111. |
| [35] | 严茹雪, 贺怡宁, 韩超, 等. 钠-葡萄糖协同转运蛋白2抑制剂与尿路感染风险的相关研究进展[J]. 中国医药导报, 2025, 22 (29): 122-126+132.doi:10.20047/j.issn1673-7210.2025.29.25. |
| [36] | American Diabetes Association Professional Practice Committee for Diabetes*. Summary of revisions: Standards of care in diabetes-2026[J]. Diabetes Care, 2026, 49(1Suppl 1): S6-S12. doi: 10.2337/dc26-SREV. |
| Viewed | ||||||
|
Full text |
|
|||||
|
Abstract |
|
|||||