临床荟萃 ›› 2026, Vol. 41 ›› Issue (10): 933-937.doi: 10.3969/j.issn.1004-583X.2026.10.010

• 论著 • 上一篇    下一篇

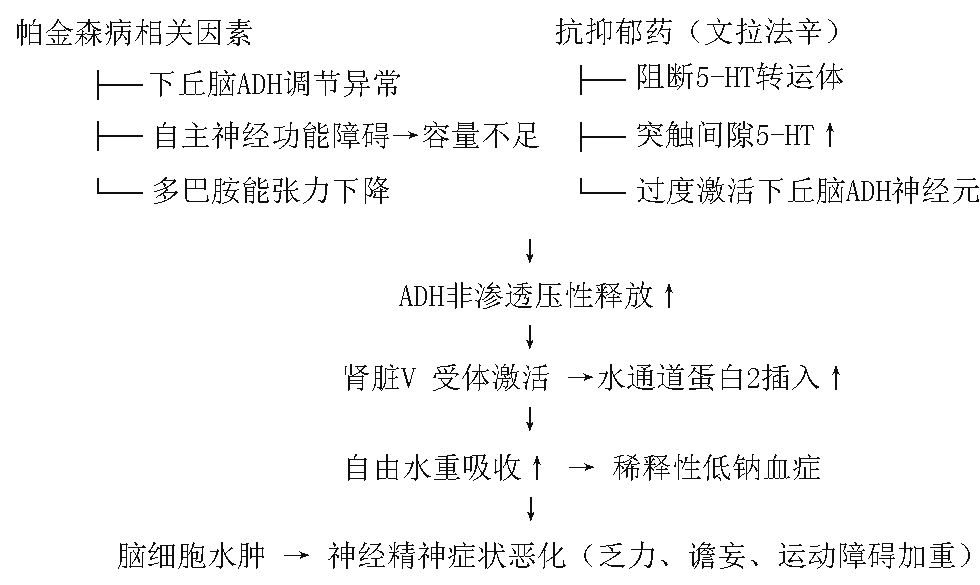
帕金森共病抑郁患者使用抗抑郁药诱发的SIADH诊治1例——精神神经融合的实践体会

胡萍1, 韩冰1,2(), 王玉平2,3,4,5   

  1. 1 河北医科大学第一医院 精神科, 河北 石家庄 050023
    2 首都医科大学宣武医院河北医院 神经内科, 河北 石家庄 050000
    3 河北省神经医学技术创新中心, 河北 石家庄 050000
    4 心身医学河北省工程研究中心, 河北 石家庄 050000
    5 首都医科大学宣武医院 神经内科, 北京 100032
  • 收稿日期:2026-10-01 出版日期:2026-10-20 发布日期:2026-10-10
  • 通讯作者: 韩冰 E-mail:hanbing1987@hebmu.edu.cn

Diagnosis and management of antidepressant-induced SIADH in a patient with Parkinson's disease and comorbid depression: A case report and insights from integrated psychiatric and neurological care

Hu Ping1, Han Bing1,2(), Wang Yuping2,3,4,5   

  1. 1 Department of Psychiatry, the First Hospital of Hebei Medical University, Shijiazhuang 050023, China
    2 Department of Neurology, Xuanwu Hospital of Capital Medical University Hebei Hospital, Shijiazhuang 050000, China
    3 Neuromedical Technology Innovation Center of Hebei Province, Shijiazhuang 050000, China
    4 Hebei Provincial Engineering Research Center for Psychosomatic Medicine, Shijiazhuang 050000, China
    5 Department of Neurology, Xuanwu Hospital Capital Medical University, Beijing 100032, China
  • Received:2026-10-01 Online:2026-10-20 Published:2026-10-10
  • Contact: Han Bing E-mail:hanbing1987@hebmu.edu.cn

摘要:

目的 探讨帕金森综合征与焦虑抑郁共病患者使用抗抑郁药诱发抗利尿激素不适当分泌综合征(SIADH)的临床特点及诊治策略,从精神神经融合角度总结共病患者的诊疗体会。方法 回顾1例在帕金森综合征背景下,抗抑郁方案调整为文拉法辛后出现严重低钠血症患者的临床资料,结合文献从药理学机制、临床特征及管理策略等方面进行分析。结果 患者为70岁男性,因焦虑抑郁状态长期接受抗抑郁治疗,换用文拉法辛后出现严重低钠血症(血钠126 mmol/L),表现为双下肢无力加重、精神差、言语不清,与帕金森病进展及抑郁复发难以区分。实验室检查符合SIADH诊断。停用文拉法辛并补钠治疗后血钠恢复正常,神经精神症状明显改善。文献复习共纳入类似共病病例4例,均为个案报道,普遍存在诊断延迟。结论 帕金森综合征与焦虑抑郁共病患者使用5-羟色胺和去甲肾上腺素再摄取抑制剂(SNRIs)、5-羟色胺再摄取抑制剂(SSRIs)类药物存在诱发SIADH的显著风险。此类患者出现无法解释的神经精神症状恶化时,应首先排除低钠血症等代谢因素,常规监测血钠水平,采用多学科协作管理。

关键词: 抑郁症, 抗利尿激素不适当分泌综合征, 低钠血症, 文拉法辛, 帕金森综合征, 精神神经融合

Abstract:

Objective To investigate the clinical characteristics and management strategies of antidepressant-induced syndrome of inappropriate antidiuretic hormone secretion (SIADH) in patients with comorbid parkinsonism and anxiety/depression, and to summarize clinical experience in the diagnosis and management of such comorbid conditions from an integrated neuropsychiatric perspective. Methods The clinical data of a patient with parkinsonism who developed severe hyponatremia after the antidepressant regimen was switched to venlafaxine were retrospectively reviewed. The case was analyzed in conjunction with the relevant literature, with a focus on pharmacological mechanisms, clinical manifestations, and management strategies. Results The patient was a 70-year-old man who had received long-term antidepressant treatment for anxiety and depression. After switching to venlafaxine, he developed severe hyponatremia (serum sodium, 126 mmol/L), manifested by worsening bilateral lower-extremity weakness, poor mental status, and dysarthria. These manifestations were difficult to distinguish from progression of Parkinson's disease and recurrence of depression. Laboratory findings were consistent with a diagnosis of SIADH. After discontinuation of venlafaxine and sodium supplementation, serum sodium levels returned to normal, accompanied by marked improvement in neuropsychiatric symptoms. A literature review identified 4 similar cases of comorbid conditions, all reported as individual case reports, with delayed diagnosis being a common feature. Conclusion Patients with comorbid parkinsonism and anxiety/depression are at substantial risk of developing SIADH when treated with serotonin and norepinephrine reuptake inhibitors (SNRIs) or selective serotonin reuptake inhibitors (SSRIs). When unexplained worsening of neuropsychiatric symptoms occurs in such patients, metabolic abnormalities such as hyponatremia should be ruled out first. Routine monitoring of serum sodium levels and multidisciplinary collaborative management are recommended.

Key words: depressive disorder, syndrome of inappropriate antidiuretic hormone secretion, hyponatremia, venlafaxine, parkinsonism, psychoneurological integration

中图分类号: